Seasonal influenza is an entirely predictable disruption governed by precise immunological kinetics, transmission vectors, and operational bottlenecks. While public health messaging routinely reduces annual preparation to vague admonitions about hygiene and vaccination, managing seasonal pathogen circulation requires treating viral containment as a supply chain, capacity, and risk-management challenge. Households and organizations experience predictable failure modes during peak viral windows not because of a lack of intent, but due to poorly structured interventions deployed at incorrect inflection points. Deconstructing the mechanics of influenza spread reveals the structural vulnerabilities in standard preparation models and provides a rigorous framework for systematic mitigation.
The Transmission Function and Environmental Vector Mechanics
Viral reproduction and transmission operate within a bounded system defined by absolute variables: viral shedding rates, aerosol persistence, mucosal contact efficiency, and host susceptibility. Influenza A and B viruses survive on hard surfaces for up to 48 hours, though transfer efficiency to human skin degrades exponentially past the two-hour mark. Airborne transmission via respiratory droplets operates as a function of indoor relative humidity and ventilation rates. Indoor relative humidity maintained below 40 percent increases aerosol suspension time and desiccates human mucosal membranes, impairing the ciliary escalator mechanism responsible for clearing particulate matter from the upper respiratory tract. For a different look, see: this related article.
Mitigating baseline transmission risk requires shifting focus from surface disinfection to environmental modification and airflow management. High-efficiency particulate air filtration and targeted carbon dioxide monitoring provide quantifiable proxies for indoor viral accumulation. When indoor carbon dioxide concentrations exceed 800 parts per million in a shared residential or commercial space, stale air volume indicates insufficient air changes per hour, creating an environment primed for viral superspreading events. Preparation must begin not with purchasing disinfectants, but with engineering baseline ventilation parameters before seasonal temperatures force indoor enclosure.
The Timing and Immunological Mechanics of Vaccination
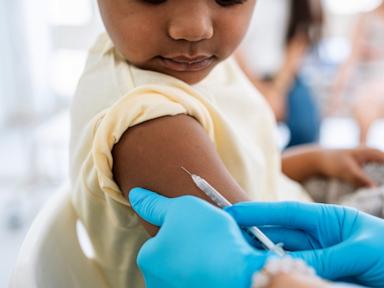
The seasonal influenza vaccine functions as a probabilistic defense mechanism rather than a sterile barrier. Because circulating strains mutate via antigenic drift, formulation matching relies on surveillance data collected months prior by global networks. The efficacy coefficient fluctuates annually between 40 and 60 percent against medically attended illness, depending on the immunological distance between vaccine strains and circulating variants. Related insight on this trend has been shared by Medical News Today.
Evaluating the utility of vaccination requires analyzing the timing function of antibody kinetics. Following inoculation, human seroconversion requires approximately 14 days to reach peak neutralizing antibody titers. Consequently, administering the vaccine after community transmission metrics surge results in a vulnerability window during which the population remains unprotected while viral load increases exponentially. Optimal deployment occurs strictly ahead of the historical inflection curve—typically late September or October in the Northern Hemisphere—to ensure peak titers align with early community exposure.
Furthermore, immunosenescence in older populations and variable response rates in pediatric cohorts necessitate stratified risk assessment within households. High-dose and adjuvanted formulations designed for geriatric populations compensate for reduced B-cell responsiveness, while multi-dose pediatric schedules require precise adherence to interval timelines to achieve full seroprotection. Treating vaccination as an administrative checkbox rather than a time-sensitive immunological deployment leads directly to institutional and household failure.
Resource Allocation and Household Operational Buffers
Operational resilience during a pathogen wave depends on resource pre-positioning and supply chain redundancy. When community illness rates peak, local pharmacies experience simultaneous spikes in demand for diagnostics, therapeutics, and symptomatic relief agents, creating localized supply chain collapses.
Effective household preparation establishes a dedicated reserves inventory categorized by functional utility:
- Diagnostic Validation: Molecular and antigen-based testing supplies to differentiate influenza from competing respiratory pathogens such as SARS-CoV-2 and respiratory syncytial virus. Accurate identification dictates whether targeted antiviral interventions are clinically indicated.
- Pharmacological Interventions: Neuraminidase inhibitors, specifically oseltamivir, operate under a strict time-dependent efficacy window. These agents must be administered within 48 hours of symptom onset to truncate viral replication cycles and reduce the duration of systemic symptoms by approximately one to two days. Stockpiling these medications requires pre-established clinician pathways rather than emergency acquisition during active infection.
- Symptom Management and Hydration Infrastructure: Electrolyte solutions, antipyretics, and pulse oximetry devices to monitor physiological deterioration markers such as peripheral oxygen saturation falling below 92 percent.
The economic cost of inadequate preparation manifests as lost productivity, emergency department overcrowding, and secondary bacterial infections resulting from unmanaged primary viral insults.
The Decision Matrix for Clinical Escalation
A critical failure in standard preparation guides is the absence of objective thresholds for escalating care. Mild viral illness creates decision fatigue, leading either to premature utilization of high-acuity healthcare resources or dangerous delay in treating severe complications. Establishing a clear operational decision matrix removes ambiguity.
Primary clinical indicators requiring immediate escalation beyond home-based management include persistent dyspnea, acute chest pain, altered mental status, cyanosis, and high-grade fever unresponsive to antipyretics for exceeding 72 hours. Secondary bacterial pneumonia represents the most common severe complication of influenza, arising from viral-induced damage to the respiratory epithelium that facilitates bacterial adherence. Recognizing this transition requires tracking the biphasic illness curve: an initial period of viral symptoms followed by temporary improvement, subsequently superseded by a sudden resurgence of high fever, productive cough, and pleuritic chest pain.
Strategic Resource Deployment
Systematic preparation for seasonal pathogen waves requires treating health management as an exercise in risk mitigation and logistical sequencing. By optimizing indoor ventilation before seasonal drops in humidity, executing vaccination schedules strictly ahead of epidemiological inflection points, maintaining pre-positioned pharmaceutical reserves, and defining quantitative escalation thresholds, households and organizations eliminate the vulnerability vectors that turn predictable seasonal phenomena into operational crises.



